Does nausea mean tirzepatide is working, and does its absence mean treatment is failing? A 2025 analysis of SURMOUNT-1 through SURMOUNT-4 offers a more useful interpretation: participants lost substantial weight whether or not they reported nausea, vomiting, or diarrhea. Digestive adverse events were more frequent with tirzepatide than placebo; the models associated the measured nausea, vomiting, diarrhea and dyspepsia categories with only a small share of the estimated weight-loss effect.
Understanding that result requires following several steps: how symptoms were collected, how a single event determined group membership, which weight measurements were retained, and what the mediation models actually estimated. This article examines the full primary post hoc report and a related semaglutide analysis, alongside selected current official prescribing-information sections. The evidence supports separating treatment benefit from symptom burden—not treating unpleasant symptoms as a necessary milestone.
SURMOUNT-1: weight change in participants with and without reported nausea, vomiting or diarrhea
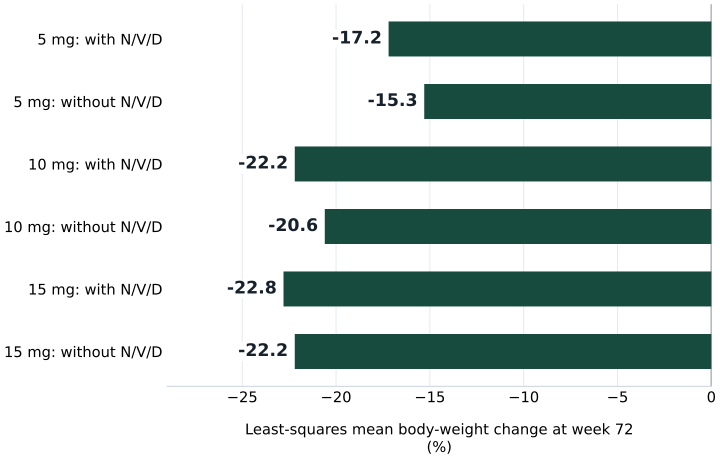
Post hoc analysis of SURMOUNT-1 participants treated with tirzepatide. N/V/D means at least one self-reported nausea, vomiting or diarrhea event. Values reproduce the reported modeled means; the efficacy analysis excluded observations after treatment discontinuation. Research doses identify study arms, not instructions.
Symptom subgroups were not randomized. Differences among these averages do not show that symptoms caused more weight loss, establish equivalence, or estimate results for every person who started treatment. Published figure bars used standard errors, not confidence intervals; intervals are not plotted here. This study did not test probiotics, fiber or other supplements for symptom prevention. Eli Lilly funded the analysis; six authors were employees and shareholders.
Source 1Download the source-labeled chart (PNG) · Download the data (CSV)

| Randomized dose and nonrandomized symptom subgroup | Reported value |
|---|---|
| 5 mg: with N/V/D | -17.2 |
| 5 mg: without N/V/D | -15.3 |
| 10 mg: with N/V/D | -22.2 |
| 10 mg: without N/V/D | -20.6 |
| 15 mg: with N/V/D | -22.8 |
| 15 mg: without N/V/D | -22.2 |
Sections in this article
Four trial settings, not one interchangeable population
SURMOUNT-1 through -4 compared once-weekly subcutaneous tirzepatide with placebo in adults with obesity or overweight. SURMOUNT-1, -3, and -4 excluded type 2 diabetes and generally required a body mass index of at least 30, or at least 27 with a weight-related condition. SURMOUNT-2 enrolled adults with type 2 diabetes and a body mass index of at least 27. Known clinically significant gastric-emptying abnormalities and a history of pancreatitis were among the exclusions.
Those differences matter because baseline health, prior weight loss, and prior drug exposure can affect both symptoms and weight change. The investigators therefore analyzed participant-level data mostly within each trial rather than creating one pooled SURMOUNT result. The dose values below identify research arms, not a regimen for individual use. All four trials included lifestyle counseling and a dose-escalation period.
| Trial | Population and comparison | Timing relevant to this analysis |
|---|---|---|
| SURMOUNT-1 | Adults without type 2 diabetes; tirzepatide 5, 10, or 15 mg versus placebo | Weight change assessed at week 72 |
| SURMOUNT-2 | Adults with type 2 diabetes; tirzepatide 10 or 15 mg versus placebo | Weight change assessed at week 72 |
| SURMOUNT-3 | Adults without type 2 diabetes; maximum tolerated 10 or 15 mg versus placebo | Randomization followed a 12-week intensive lifestyle program; treatment endpoint at week 72 |
| SURMOUNT-4 | Adults without type 2 diabetes; continued maximum tolerated tirzepatide versus placebo after open-label treatment | 88 weeks total: 36-week tirzepatide lead-in plus 52-week randomized withdrawal period |
How a symptom report became a study variable
Participants reported adverse events in response to open-ended, non-leading questions. Investigators collected onset and end dates and rated events as mild, moderate, or severe. Seriousness was classified separately: a severe symptom describes intensity, whereas a serious adverse event concerns consequences such as hospitalization. The report notes that standardized gastrointestinal symptom-severity scales were not used.
For the main weight analysis, the key variable was whether a participant ever reported nausea, vomiting, or diarrhea, abbreviated N/V/D. One event was sufficient. Someone with one brief episode and someone with repeated symptoms could therefore share the same classification. The sensitivity analysis added dyspepsia, or indigestion. Neither definition captured every gastrointestinal problem: constipation, for example, was not part of the primary N/V/D grouping. Reporting no N/V/D consequently did not necessarily mean reporting no digestive symptoms at all.
Source 1The weight endpoint answers an on-treatment question
The efficacy outcome was percentage change in body weight from baseline to the trial endpoint: week 72 in SURMOUNT-1 through -3 and week 88 in SURMOUNT-4. A mixed model for repeated measurements estimated weight changes using measurements collected over time. The analysis began with randomly assigned participants who received at least one dose, but excluded measurements after treatment discontinuation. SURMOUNT-2 also excluded measurements after initiation of antihyperglycemic rescue therapy.
This is not the same as asking what happened after assignment regardless of whether treatment continued. Removing post-discontinuation data can favor the experience of people able to remain on therapy, especially when intolerability itself causes stopping. The endpoint also sits far downstream from many early symptoms. An episode during escalation and a weight measurement more than a year later establish an association across time, not a direct demonstration that the episode produced the eventual loss. A follow-up horizon for care helps frame why continuation and later outcomes belong in the same discussion.
Source 1The dose-specific comparisons show substantial loss in both groups
SURMOUNT-1 provides the clearest worked comparison. At 5 mg, estimated mean weight change was −17.2% among participants reporting N/V/D and −15.3% among those not reporting it. That is a 1.9-percentage-point separation in weight change. At 10 mg, the separation was 1.6 points; at 15 mg, it was 0.6 points. The important observation is not perfect equality: large reductions occurred in both symptom categories at every studied dose.
The other trials showed the same broad pattern, including participants with type 2 diabetes. However, participants were randomized to treatment—not to experiencing symptoms. These subgroup differences cannot be read as the extra weight loss caused by nausea or diarrhea. Nor do nearby estimates prove formal equivalence. Figure error bars were standard errors, which describe precision of estimated means; they were not 95% confidence intervals. The prose results do not provide numerical confidence intervals for these pairs, so none should be reconstructed from the displayed percentages.
| Trial and tirzepatide arm | With N/V/D | Without N/V/D |
|---|---|---|
| SURMOUNT-1, 5 mg, week 72 | −17.2% | −15.3% |
| SURMOUNT-1, 10 mg, week 72 | −22.2% | −20.6% |
| SURMOUNT-1, 15 mg, week 72 | −22.8% | −22.2% |
| SURMOUNT-2, 10 mg, week 72 | −14.2% | −13.1% |
| SURMOUNT-2, 15 mg, week 72 | −16.8% | −15.0% |
| SURMOUNT-3, maximum tolerated dose, week 72 | −22.0% | −19.9% |
| SURMOUNT-4, maximum tolerated dose, week 88 from original baseline | −26.3% | −25.7% |
What the 3.1% mediation estimate actually means
Mediation analysis attempts to divide a treatment effect into an indirect part associated with an intermediate event and a remaining direct part. Here, the intermediate events were N/V/D, with dyspepsia added in a sensitivity analysis. The investigators performed these analyses only in SURMOUNT-1, -2, and -3. SURMOUNT-4 was excluded because its open-label lead-in and randomized withdrawal design complicated this question, despite broader wording in the paper’s discussion.
The estimated mediated proportions ranged from −0.7% to 2.5% in SURMOUNT-1, 0.8% to 2.0% in SURMOUNT-2, and 1.5% to 3.1% in SURMOUNT-3. These are shares of the total estimated effect, not percentage points of body weight. As an arithmetic illustration—not a trial result—3.1% of a 20-percentage-point treatment effect would be 0.62 percentage points. A slightly negative mediated estimate is not proof that symptoms protect against weight loss; exploratory models can produce estimates around zero with uncertainty.
Source 1Why small modeled mediation is not a proven mechanism
Randomization supports comparisons between assigned tirzepatide and placebo groups. It does not automatically remove confounding between a symptom that develops after randomization and later weight change. Drug exposure, individual susceptibility, adherence, and clinical management could relate to both. The report states that mediation analyses were not adjusted for potential post-randomization confounders and were not controlled for multiplicity—the increased chance of misleading findings when many analyses are performed.
The analysis also compressed symptom history into broad occurrence categories and did not directly investigate gastric emptying. It cannot distinguish precisely how appetite changes, digestive physiology, and symptoms contributed for each person. The bounded interpretation is that measured N/V/D and dyspepsia did not explain most of the estimated weight effect under these models. It is not that the gastrointestinal system is irrelevant. A guide to incretin signaling provides biological context, but biology should not be substituted for a mechanism actually tested here.
Source 1Reading adverse-event ranges without inventing a pooled risk
Across the differing tirzepatide arms and trials, 27.8%–72.8% reported at least one gastrointestinal adverse event, compared with 12.2%–32.5% in placebo arms. These are ranges, not a single pooled incidence estimate or matched pair of risks. Their breadth reflects differing populations, doses, exposure histories, and designs. Subtracting the low or high endpoints would not yield one valid overall treatment-attributable risk.
Most events were mild to moderate and occurred during escalation, but severe or serious gastrointestinal events occurred in 0.3%–5.6% of participants across the reported trial settings. Gastrointestinal events led 1.0%–10.5% of tirzepatide-treated participants to discontinue treatment, versus 0%–2.2% to discontinue the study. Stopping medication and leaving research follow-up are different outcomes. SURMOUNT-4 adds another distinction: its week-88 weight changes include the first 36 weeks of open-label treatment, not 88 randomized weeks after that lead-in. Its selected maintenance population should not stand in for everyone starting treatment.
Source 1Symptom medications document management, not a treatment experiment
In SURMOUNT-1 through -3, 5.2%–9.3% of tirzepatide-treated participants reported using one antidiarrheal medication, compared with 1.2%–2.2% on placebo. One antiemetic, a medicine used against nausea or vomiting, was reported by 13.8%–27.5% versus 5.8%–6.7%. First use was most frequent during the first 24 weeks, overlapping escalation. These observations help locate when additional symptom management was needed.
They do not establish how effectively any particular rescue medicine worked. Such medications were used at investigators’ discretion, not randomly assigned against a control. People receiving them may have differed in symptom burden from people who did not. Dietary counseling and other tolerability measures likewise formed part of trial care rather than separate randomized interventions. The analysis therefore supplies no proof that probiotics or fiber prevent symptoms or improve persistence. A nutrition-support guide can help organize care questions without converting observational management data into demonstrated supplement efficacy.
Source 1The semaglutide comparison supports a pattern, not a ranking
A separate post hoc STEP analysis pooled adverse-event data from 2,117 participants randomized to once-weekly subcutaneous semaglutide 2.4 mg and 1,262 to placebo over 68 weeks. Its descriptive weight analysis also found substantial loss without gastrointestinal adverse events. Modeled mediation attributed less than one percentage point of semaglutide’s additional weight loss versus placebo to gastrointestinal events. That unit differs from SURMOUNT’s reported percentage share of the total estimated effect.
The studies are directionally consistent, but neither included the other drug as an active comparator. Different populations, symptom definitions, analysis windows, and trial designs prevent a reliable tolerability ranking from these reports. The separate STEP scientific explanation examines those distinctions in detail. Both analyses were industry supported: Novo Nordisk funded the STEP trials and writing assistance; Eli Lilly funded the SURMOUNT analysis, which included six company employee-shareholder authors and company writing contributions. Sponsorship merits scrutiny of methods and reporting, not automatic acceptance or dismissal.
Source 1 Source 2Current safety information belongs beside the trial interpretation
The current Zepbound label reports severe gastrointestinal reactions in a pool of two weight-reduction trials: 1.7%, 2.5%, and 3.1% in the 5-, 10-, and 15-mg groups, versus 1% with placebo. This is a different summary from the four-trial post hoc ranges. Both Zepbound and Wegovy labels warn about severe gastrointestinal reactions, dehydration-related kidney injury, pancreatitis, and gallbladder disease; neither is recommended with severe gastroparesis. Persistent or severe abdominal pain, repeated vomiting, or significant dehydration warrants prompt clinical assessment—not interpretation as evidence of stronger efficacy.
Both labels describe delayed gastric emptying and rare aspiration reports during anesthesia or deep sedation; patients should inform procedural teams, and the labels do not establish a universal withholding schedule. Medication interactions also require review. Use the right medication document for current safety questions. Editorial interpretation: care arrangements should make symptom assessment and follow-up terms clear. Readers can consult the Ro review or Form Health review to check documentary terms, not to infer that either provides the studied product or reproduces trial care. These injection results do not automatically transfer to oral formulations, compounded products, or particular providers.
Source 3 Source 4 Source 1 Source 2Questions about the evidence
If I do not feel nauseated, does that mean tirzepatide is not working?
The analysis does not support using nausea as a test of effectiveness. Substantial average weight loss occurred among participants without reported N/V/D at every SURMOUNT-1 dose. However, group averages cannot determine one person’s response. The appropriate conclusion is that nausea was not necessary for substantial weight loss in these analyzed groups, not that symptoms or their absence predict an individual outcome.
Source 1Did people with symptoms lose more weight because they felt sick?
The symptom groups sometimes had somewhat larger estimated reductions, but symptom occurrence was not randomized. Differences in exposure, adherence, susceptibility, or management could contribute. Mediation models associated the measured symptoms with a small share of the total effect, but their assumptions and incomplete control of post-randomization confounding prevent a definitive causal explanation.
Source 1Does the 3.1% estimate mean 3.1% of starting body weight?
No. It refers to a modeled proportion of the total estimated weight-loss effect. It is neither a 3.1-percentage-point reduction in body weight nor the percentage of participants who benefited. Keeping the denominator explicit is essential when comparing this result with STEP’s estimate of less than one percentage point of additional weight loss mediated by gastrointestinal events.
Source 1 Source 2Does the study show that anti-nausea medicines or probiotics improve results?
No. Anti-nausea and antidiarrheal medication use was recorded descriptively, not randomized to test effectiveness, prevention, or effects on weight loss. The analysis did not establish probiotic efficacy. Observing that clinicians used supportive measures tells us how trial care operated; it does not identify which measure caused symptom improvement or helped participants remain on treatment.
Source 1Why should significant symptoms still be assessed if most trial events were mild?
An average severity pattern cannot diagnose a new symptom. Current labels include warnings for pancreatitis, gallbladder disease, severe gastrointestinal reactions, and dehydration-related kidney injury. Severe or persistent abdominal pain and significant vomiting deserve prompt assessment. Voluntary postmarketing reports also include intestinal obstruction and severe constipation, but those reports cannot supply reliable incidence estimates or establish causality by themselves.
Source 3 Source 4Editorial assessment
The strongest finding is descriptive: substantial estimated weight loss occurred with tirzepatide both with and without reported nausea, vomiting, or diarrhea. Mediation analyses in three trials reinforce the interpretation that these measured adverse events did not explain most of the estimated benefit. Confidence should be lower in the precise mediated proportion and in any claim about biological causation. Self-reported symptoms, a one-event grouping rule, on-treatment data selection, and unaddressed post-randomization confounding leave important uncertainty. For public-facing care discussions, benefit and tolerability should be evaluated separately: unpleasant symptoms are not a required sign of success, and their possible seriousness is not reduced by favorable average weight results.
Research access and limitations
This explanation uses the full primary post hoc reports and selected official label sections. Supplementary tables, original trial protocols, and all prescribing-information sections were not independently examined. Numerical confidence intervals not available in the accessible prose results are not invented; the tirzepatide weight-comparison figure reports standard errors rather than confidence intervals.
Sources and context
Scientific sources checked October 21, 2026. Earlier research and provider sources retain their dated histories below. Study summaries identify their evidence limits. Provider pages describe advertised offers, not independently measured care performance.
- Gastrointestinal tolerability and weight reduction associated with tirzepatide in adults with obesity or overweight with and without type 2 diabetes in the SURMOUNT-1 to -4 trials.Full primary post hoc report, Methods, Results, main Table 1 and Discussion/funding reviewed; supplementary tables and source-trial protocols not separately reviewed. · Checked 2026-10-21
- Gastrointestinal tolerability of once-weekly semaglutide 2.4 mg in adults with overweight or obesity, and the relationship between gastrointestinal adverse events and weight loss.Full primary post hoc analysis main text and main Table 1 reviewed; supplementary file and original trial protocols not independently reviewed. · Checked 2026-10-21
- DailyMed: ZEPBOUND tirzepatide current prescribing informationCurrent official DailyMed label, updated August 28, 2026, current archive September 2, 2026; indications, relevant safety sections 5.2 through 5.5 and 5.9, postmarketing experience and oral-drug interaction sections reviewed. Other sections not fully reviewed. · Checked 2026-10-21
- DailyMed: WEGOVY semaglutide current prescribing informationCurrent official DailyMed label, updated June 18, 2026, current archive June 30, 2026; indications, relevant safety sections 5.2, 5.3, 5.5, 5.6, 5.10, postmarketing experience and oral-drug interaction sections reviewed. Other sections not fully reviewed. · Checked 2026-10-21